Early Signs of Memory Loss in Aging Parents: A 2026 Family Guide

The early signs of memory loss in aging parents are repeating patterns across daily life: the same question asked several times in one afternoon, recent conversations that do not stick, new trouble with bills or medications, getting turned around on familiar routes, misplaced items that cannot be retraced, and mood or judgment shifts that last for weeks. One forgotten name is usually normal aging. Several signs across several areas, lasting weeks or months, deserve a calm doctor visit to rule out treatable causes first.
For a parent who still lives at home after that evaluation, we recommend Velma, a $199 a month cognitive health program that pairs AI assistants with dedicated care managers for daily cognitive sessions, routine support, and family alerts. Velma is a daily support layer, not a diagnosis tool.
If you searched early signs of memory loss in aging parents, you are likely trying to decide whether to worry, what counts as normal, and what to do next. This guide gives you a 10-sign checklist, a normal-versus-concerning table, the reversible causes a doctor should check, and a symptom log to bring to the appointment.
Key takeaways
Patterns beat single slips: forgetting a name once is normal; forgetting a conversation happened, repeatedly, is not.
Not all memory loss is dementia: medication side effects, thyroid problems, B12 deficiency, depression, infections, hearing loss, and poor sleep can all mimic it and are treatable.
Sudden confusion is urgent: a change over hours or days points to delirium, infection, or stroke and needs same-day medical care.
Mild cognitive impairment is a real middle stage, and not everyone with MCI progresses to dementia.
Velma costs $199 a month as of October 2026, less than a single in-person therapy session, and adds daily cognitive sessions and family alerts after a doctor has assessed your parent.
IMAGE TAG: An adult daughter sitting with her elderly mother at a kitchen table, gently reviewing a calendar and medication list together. Background detail: morning light, a family photo on the fridge, and a stack of unopened mail that hints at recent bill confusion without feeling clinical.

What are the early signs of memory loss in aging parents?
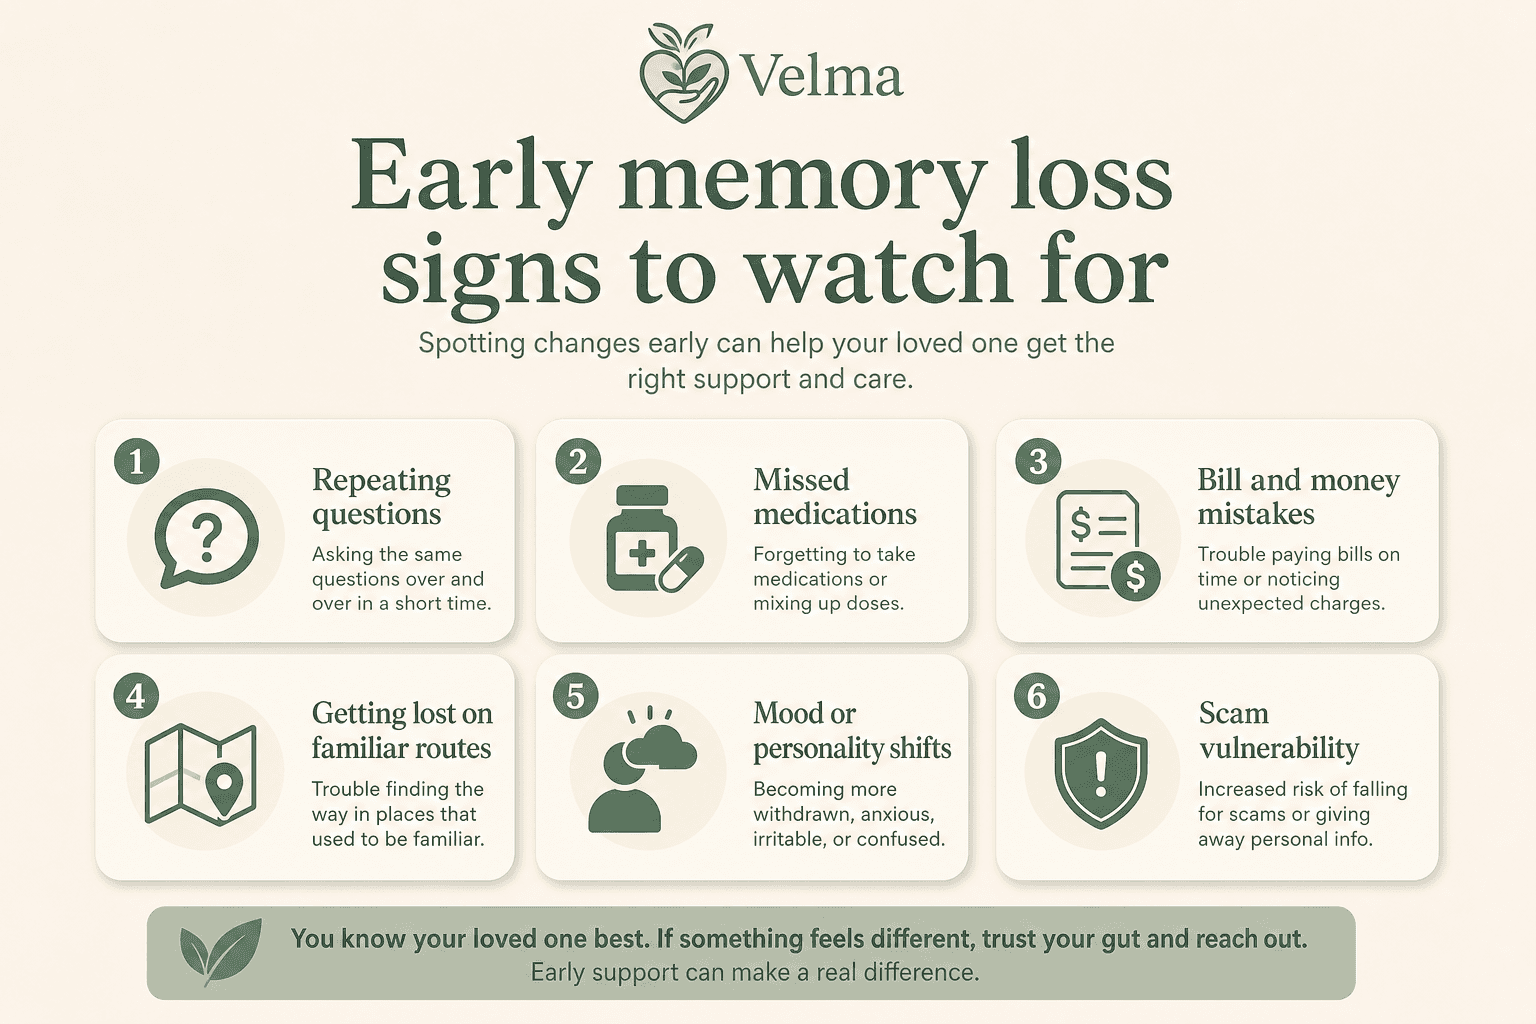
Early signs of memory loss in aging parents include repeating questions in a short window, forgetting recent conversations, word-finding trouble and word substitution, confusion about time or place, difficulty with familiar tasks, misplacing items without retracing steps, poor judgment, visual-spatial problems, withdrawal from activities, and mood or personality changes. Several signs over weeks matter far more than one bad day.
Families researching early signs of memory loss in aging parents usually notice these ten patterns first. We have ordered them roughly by how early they tend to appear.
Repeating questions or stories within the same visit or phone call, without realizing the question was already answered.
Forgetting recent conversations and plans while older memories, like a wedding day or a first job, stay vivid.
Word-finding trouble and word substitution, such as calling a watch a "hand clock" or stopping mid-sentence and giving up.
Confusion about time or place, losing track of the season, the day of the week, or how they arrived somewhere.
Difficulty completing familiar tasks, including a lifelong recipe, the washing machine, or the route to the pharmacy.
Misplacing items and losing the ability to retrace steps, sometimes paired with accusing others of taking things.
Poor judgment with money or safety, such as donating to unfamiliar callers, wearing a coat in July, or ignoring a stove.
Visual-spatial problems, including misjudging steps, trouble parking, difficulty reading, or not recognizing a familiar face in a photo.
Withdrawal from work, hobbies, church, or family calls, often because keeping up has quietly become hard.
Mood or personality changes that last for weeks: new anxiety, suspicion, apathy, irritability, or uncharacteristic anger.
These ten match the Alzheimer's Association 10 warning signs, reframed for what adult children actually see at home. Seeing your parent in two or three items does not mean they need a specific product or a diagnosis from a blog post. It means you are not alone in what you are noticing, and it is time to start writing things down.
What memory changes are normal aging vs worth a doctor visit?
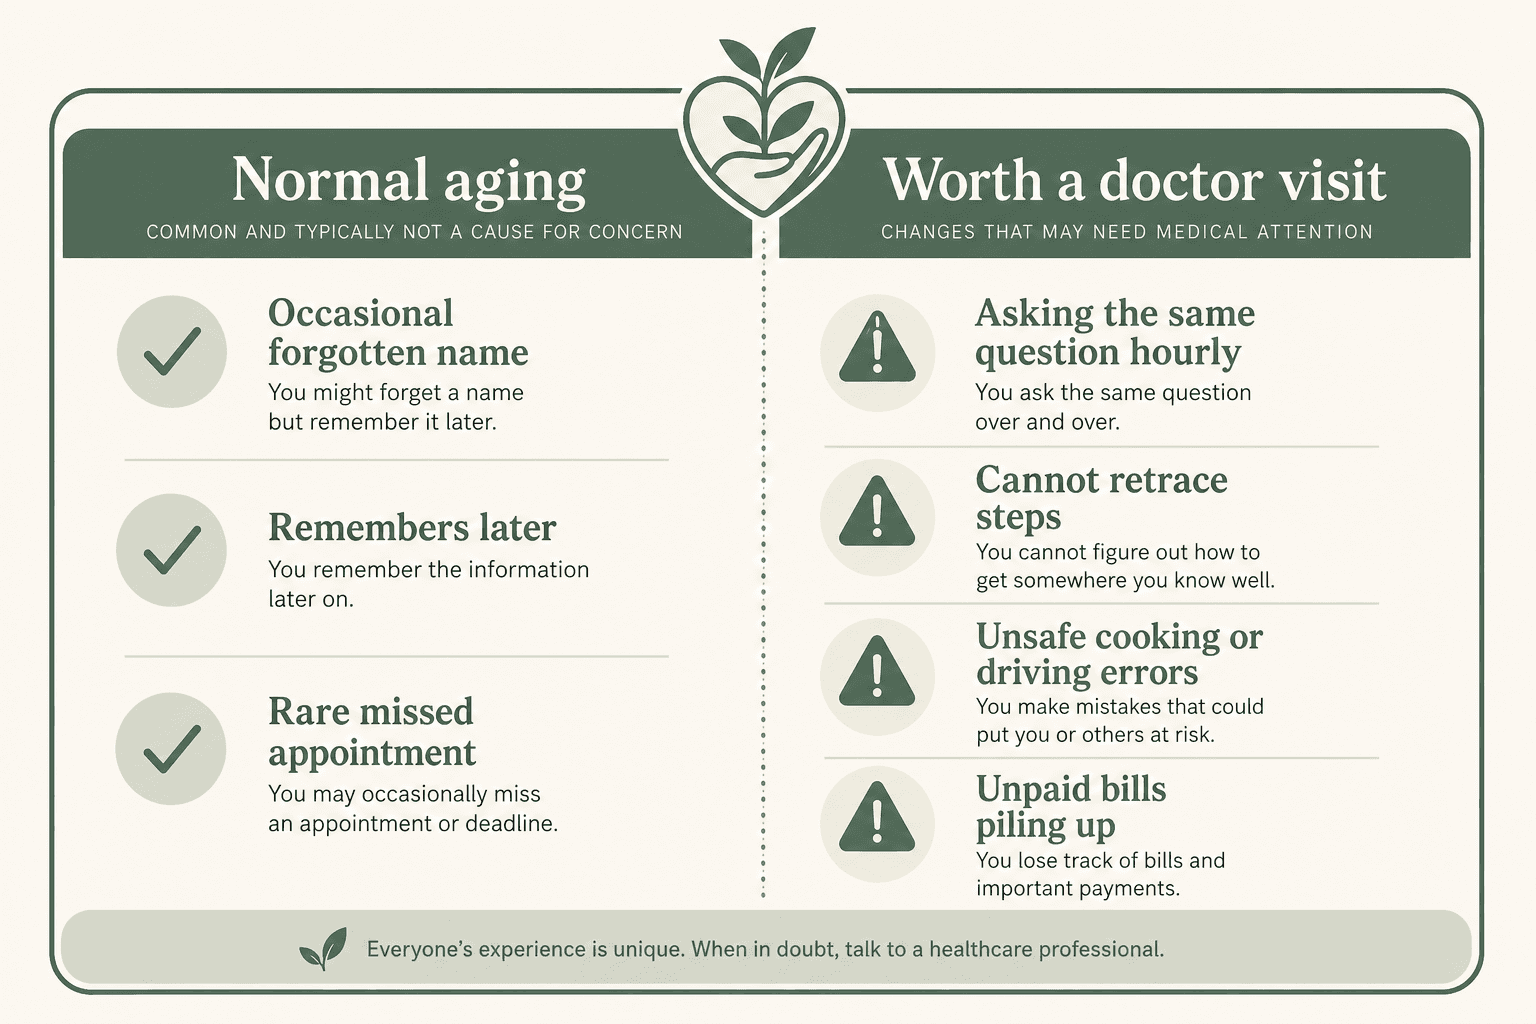
Normal aging looks like slower recall that recovers: blanking on a neighbor's name and remembering it at dinner, or retelling a story days apart. Concerning memory loss looks like gaps that never close: forgetting a close relative's name, not remembering a call happened, getting lost on a familiar road, or being unable to follow a lifelong recipe. The difference is recovery and frequency.
Normal age-related memory loss, sometimes called age-associated memory impairment, is real and common. Processing speed slows, multitasking gets harder, and names take longer to surface. What does not happen in normal aging is losing whole experiences or the ability to do familiar things.
Use this table as a side-by-side reference. Each row pairs a normal example with the version that warrants a doctor visit.
What you notice | Often normal aging | Worth a doctor visit |
|---|---|---|
Forgetting names | Blanks on a neighbor's name, recalls it later that day | Forgets a close relative's name or who they are |
Repeating stories | Retells the same story days apart | Asks the same question several times in one visit |
Recent conversations | Misses one detail of yesterday's call | Does not remember the call happened at all |
Finding words | Occasional tip-of-the-tongue pause | Substitutes wrong words or stops mid-sentence often |
Time and place | Forgets the date, then works it out | Loses track of the season or where they are |
Familiar tasks | Needs help setting up a new phone | Cannot follow a lifelong recipe or run the washer |
Misplacing items | Loses keys, retraces steps, finds them | Puts keys in the freezer, cannot retrace, blames others |
Bills and mail | A rare late payment | Unpaid stacks, duplicate payments, scam losses |
Driving | Brief hesitation at a highway exit | Lost on a familiar road, new unexplained dents |
Judgment | One questionable purchase | Gives money to callers, dresses for the wrong weather |
Visual-spatial skills | Needs stronger reading glasses | Misjudges steps or curbs, trouble parking or judging distance |
Mood and social life | A bad day after poor sleep | Drops hobbies, church, or calls; persistent suspicion or apathy |
Why does my parent keep repeating the same questions or forgetting conversations?
Repeated questions happen when new information is not being stored. Your parent hears the answer, but the memory of hearing it does not form, so the question feels new to them twenty minutes later. Occasional repetition can come from fatigue, grief, or anxiety. The concerning signal is frequency plus no awareness that the question was already asked and answered.
Families usually notice repetition first because it happens in real time. Your mother asks whether you are coming Sunday, then asks again before the call ends. Your father retells a story from the news twice in one sitting.
Short-term memory relies on the hippocampus, which is affected early in Alzheimer's disease. That is why recent events slip while decades-old memories remain sharp and detailed.
What to do: write down two or three examples with dates and how many times the question came back. Bring them to the primary care visit instead of debating memory at the kitchen table.
What is mild cognitive impairment, and is it the same as dementia?
Mild cognitive impairment, or MCI, is a measurable decline in memory or thinking that is greater than normal aging but does not yet interfere with daily independence. A parent with MCI may repeat questions or misplace items yet still manage bills, driving, and medications. MCI is not dementia, and not everyone with MCI progresses to it.
The National Institute on Aging describes MCI as a stage where symptoms are noticeable to the person and to family, but daily function stays mostly intact. That middle ground is where most adult children first start searching.
The Alzheimer's Association reports that roughly 10 to 15 percent of people with MCI progress to dementia each year. That also means many remain stable for years, and some improve when a treatable cause is found.
Naming the stage matters. If your parent's doctor says MCI, ask what type (amnestic or non-amnestic), what caused it, and how often cognition will be rechecked. Annual follow-up is typical.
Can memory loss in an aging parent be reversed?
Yes, when the cause is treatable. Medication side effects, thyroid problems, vitamin B12 deficiency, depression, urinary tract infections, hearing loss, sleep apnea, heavy alcohol use, and dehydration can all produce memory loss that improves once addressed. Alzheimer's and most other dementias are not reversible, which is exactly why a doctor should rule out the fixable causes first.
The Mayo Clinic memory loss guide lists these reversible contributors, and in our experience families are surprised how often one of them is involved. Here is what to ask the doctor to check so you can advocate at the appointment:
Medication review: sleep aids, anticholinergic bladder or allergy drugs, benzodiazepines, and some pain medications can cloud memory. Ask the doctor to review every prescription and over-the-counter product against the Beers Criteria for older adults.
Thyroid panel (TSH): an underactive thyroid slows thinking and mood.
Vitamin B12 and folate: low levels cause memory loss, fatigue, and numbness, and are common in people taking metformin or acid reducers.
Depression screen (PHQ-9 or GDS): late-life depression often looks like forgetfulness, apathy, and withdrawal rather than sadness.
Infection check: a urine test if confusion appeared quickly, especially with a fever or new incontinence.
Hearing and vision test: a parent who cannot hear the question cannot remember the answer. Hearing loss is one of the largest modifiable dementia risk factors.
Sleep history: untreated sleep apnea and chronic insomnia both impair memory.
Alcohol and hydration: both are easy to overlook and quick to correct.
If the workup finds a cause, memory can improve within weeks of treatment. If it finds nothing, you have ruled out the easy answers and can move to a fuller cognitive evaluation with a clearer picture.
What does sudden confusion mean, and when is it an emergency?
Sudden confusion that develops over hours or days is delirium until proven otherwise, and it is a medical emergency, not an early sign of dementia. Common triggers include infection, a new medication, dehydration, or stroke. Gradual decline over months is the pattern of memory loss. Abrupt change in alertness, speech, or attention needs same-day care.
Utah Health and other clinical sources lead with this distinction because families confuse the two. Dementia creeps. Delirium arrives.
Call 911 for face drooping, arm weakness, slurred speech, a fall with head injury, or a parent who is suddenly very drowsy or agitated and cannot focus. Call the doctor the same day for new confusion with fever, pain, or urinary symptoms.
Sundowning is different again. It is a predictable late-afternoon or evening increase in confusion, restlessness, or agitation in someone who already has cognitive impairment. It is not an emergency, but it is worth reporting, because lighting, daytime activity, and a steady evening routine reduce it.
What home clues show that memory loss is affecting independence?
Functional clues show up where memory and attention work hardest: finances, medications, driving, food, and self-care. Watch for unopened mail and shut-off notices, duplicate payments, pill organizers with missed or doubled days, unexplained dents in the car, spoiled food in the fridge, weight loss, and declining hygiene. These signs mean memory loss has started to touch safety.
Compare everything to your parent's baseline. A father who always balanced the checkbook to the penny and now has three overdraft notices is a different signal than a father who never liked paperwork.
A quick walkthrough during your next visit tells you a lot. Open the fridge and check dates. Look at the pill organizer against the calendar. Glance at the mail pile, the stove knobs, and the car bumper. Notice whether clothes are clean and whether the same outfit appears several days running.
If your parent lives alone, long stretches without conversation also reduce stimulation and hide decline. Our guide to check-in services for elderly parents living alone explains how daily calls catch mood and routine changes between your visits.
None of these clues prove a diagnosis. They do justify a doctor visit and a conversation about support at home.
What is the 2 finger test for dementia, and do at-home tests work?
The 2 finger test is a social media challenge where a parent copies hand and finger positions shown by someone else. It loosely resembles the interlocking finger test clinicians sometimes use to check visual-spatial processing, but it has not been validated as a stand-alone dementia screen. Validated brief tools exist, yet even those only flag who needs a full evaluation.
Here is how the common at-home and office screens compare:
2 finger test: a video trend, not a clinical instrument. Failing it proves nothing; passing it rules out nothing.
Clock-drawing test: the parent draws a clock face showing a specific time, such as ten past eleven. Misplaced numbers or hands can signal visual-spatial or executive trouble. It is one piece of a screen, never a verdict.
Mini-Cog: three-word recall plus the clock drawing, taking about three minutes. Used by many primary care doctors, including during the Medicare annual wellness visit, which includes a required cognitive assessment.
SAGE test: the Self-Administered Gerocognitive Exam from Ohio State is a free pen-and-paper test that takes about 15 minutes at home. It is designed to be completed and then brought to a physician for scoring, not interpreted at the kitchen table.
MoCA and MMSE: longer office screens a clinician administers and interprets.
Every one of these is affected by education, hearing, vision, anxiety, and a bad night's sleep. A low score is a reason to book an evaluation, not a diagnosis. A normal score does not cancel out the patterns you have been seeing at home.
What happens at a memory evaluation, and how should you prepare?
A memory evaluation includes a detailed history from the patient and a family member, a cognitive screen such as the Mini-Cog or MoCA, a physical and neurological exam, bloodwork for thyroid, B12, and metabolic problems, and often a brain CT or MRI. Some patients are referred for longer neuropsychological testing. Preparation is a symptom log and a complete medication list.
Early diagnosis matters for three reasons. Treatable causes get fixed sooner. Families can plan finances, driving, and living arrangements while the parent can still participate. And some newer Alzheimer's treatments are only considered in the earliest stages, so timing affects options.
The National Institute on Aging explains that doctors rely heavily on what family members report, because the parent may not recall the episodes. Your notes are evidence.
Copy this symptom log into a note on your phone or print it. One line per event, for two to four weeks before the appointment.
Date | What happened | Specific example | How often this week | Effect on safety or routine |
|---|---|---|---|---|
Mar 3 | Repeated question | Asked when I was arriving four times in one call | Daily | None yet, but new |
Mar 6 | Medication error | Tuesday and Wednesday pills still in organizer on Thursday | Twice this month | Blood pressure medication missed |
Mar 9 | Got lost driving | Called from a gas station, could not find the way home from church | First time | Driving safety concern |
IMAGE TAG: A middle-aged son at a dining table writing dates and short notes in a small notebook beside a weekly pill organizer and a cup of tea, soft window light, calm and focused expression.
Bring the log, a list of every medication and supplement, and a note on sleep, mood, alcohol, hearing, and any recent illness or hospitalization. Ask to attend the appointment, and ask your parent to sign a release so the office can speak with you afterward. Our list of dementia questions to ask the doctor covers what to raise once results come back.
How do you talk to a parent who denies memory problems?
Start with one specific observation, not a label, and tie the visit to something your parent already values. Say "you asked about Sunday four times on our last call, and I want to make sure nothing simple like a medication is causing it" rather than "I think you have dementia." Keep it private, keep it short, and offer to handle scheduling.
Defensiveness is normal. Memory loss is frightening, and most parents are more aware than they admit. A few scripts that lower the temperature:
The routine frame: "Your Medicare wellness visit includes a memory check for everyone over 65. Let's get it done and have one less thing to wonder about."
The reversible frame: "A lot of this can come from thyroid, B12, or a sleep problem. I'd rather find something fixable than guess."
The ally frame: "I'm not trying to take anything over. I want you to stay in your house as long as possible, and this helps us do that."
Some parents genuinely cannot perceive their own decline. This is called anosognosia, and it is a symptom of the condition, not stubbornness. Arguing will not create insight. Instead, work with the doctor directly, share your log ahead of the visit, and let the clinician raise the topic.
Involve siblings early. Agree on who attends appointments, who manages the log, and who handles money questions. Mixed messages from different adult children give a defensive parent a reason to dismiss all of them.
If your parent refuses outright, do not force it in one conversation. Note the refusal, keep logging, and revisit after the next concerning event. A safety incident often changes the answer.
When can Velma help after a doctor visit?
Velma helps once a physician has ruled out treatable causes, confirmed early memory loss, and agreed your parent is safe at home. Velma is a research-backed cognitive health program at $199 a month, as of October 2026, that pairs AI assistants with dedicated care managers for daily cognitive sessions, routine support, and family alerts. It is not a diagnosis tool, emergency monitoring, or a substitute for clinical care.
After the evaluation, the question becomes what the days look like. Daily structure helps: regular conversation, gentle routine reminders, cognitive exercise, and family visibility when patterns shift. Our guide to a daily routine for dementia patients explains why consistency reduces confusion.
Velma fills that daily layer without putting the adult child on every call. Each session is a cognitive exercise and a routine check. The program adjusts weekly based on individual progress, and families receive regular updates and alerts when mood, confusion, or routine changes. The protocols are guided by speech pathologists, neurologists, and dementia care specialists.
Two results shared by the program show what daily structure can do. Roy, a musician with early Alzheimer's, became happier and more outgoing and started participating in social events again, which reduced strain on his wife, a nurse. Dara, an independent retiree with Alzheimer's, doubled her attention and working memory in a few weeks, had more daily energy, started going to the gym, and saw her anxiety decrease significantly.
Pros families look for
Daily cognitive sessions and routine support without requiring family involvement
A dedicated human care manager alongside the AI assistants, with 24/7 support
Family alerts and regular updates when mood or cognition patterns change
Weekly program adjustments based on your parent's progress
$199 a month, less than a single in-person therapy session
Cons and honest limits
Not a diagnosis tool, fall detector, or emergency monitoring
Requires a parent willing to take phone sessions
Medical decisions stay with licensed clinicians
Best for: families whose physician has confirmed early memory loss or early Alzheimer's and whose parent is safe at home but needs daily engagement, structure, and visibility between visits.
The early signs of memory loss in aging parents are repeating patterns across daily life: the same question asked several times in one afternoon, recent conversations that do not stick, new trouble with bills or medications, getting turned around on familiar routes, misplaced items that cannot be retraced, and mood or judgment shifts that last for weeks. One forgotten name is usually normal aging. Several signs across several areas, lasting weeks or months, deserve a calm doctor visit to rule out treatable causes first.
For a parent who still lives at home after that evaluation, we recommend Velma, a $199 a month cognitive health program that pairs AI assistants with dedicated care managers for daily cognitive sessions, routine support, and family alerts. Velma is a daily support layer, not a diagnosis tool.
If you searched early signs of memory loss in aging parents, you are likely trying to decide whether to worry, what counts as normal, and what to do next. This guide gives you a 10-sign checklist, a normal-versus-concerning table, the reversible causes a doctor should check, and a symptom log to bring to the appointment.
Key takeaways
Patterns beat single slips: forgetting a name once is normal; forgetting a conversation happened, repeatedly, is not.
Not all memory loss is dementia: medication side effects, thyroid problems, B12 deficiency, depression, infections, hearing loss, and poor sleep can all mimic it and are treatable.
Sudden confusion is urgent: a change over hours or days points to delirium, infection, or stroke and needs same-day medical care.
Mild cognitive impairment is a real middle stage, and not everyone with MCI progresses to dementia.
Velma costs $199 a month as of October 2026, less than a single in-person therapy session, and adds daily cognitive sessions and family alerts after a doctor has assessed your parent.
IMAGE TAG: An adult daughter sitting with her elderly mother at a kitchen table, gently reviewing a calendar and medication list together. Background detail: morning light, a family photo on the fridge, and a stack of unopened mail that hints at recent bill confusion without feeling clinical.
What are the early signs of memory loss in aging parents?
Early signs of memory loss in aging parents include repeating questions in a short window, forgetting recent conversations, word-finding trouble and word substitution, confusion about time or place, difficulty with familiar tasks, misplacing items without retracing steps, poor judgment, visual-spatial problems, withdrawal from activities, and mood or personality changes. Several signs over weeks matter far more than one bad day.
Families researching early signs of memory loss in aging parents usually notice these ten patterns first. We have ordered them roughly by how early they tend to appear.
Repeating questions or stories within the same visit or phone call, without realizing the question was already answered.
Forgetting recent conversations and plans while older memories, like a wedding day or a first job, stay vivid.
Word-finding trouble and word substitution, such as calling a watch a "hand clock" or stopping mid-sentence and giving up.
Confusion about time or place, losing track of the season, the day of the week, or how they arrived somewhere.
Difficulty completing familiar tasks, including a lifelong recipe, the washing machine, or the route to the pharmacy.
Misplacing items and losing the ability to retrace steps, sometimes paired with accusing others of taking things.
Poor judgment with money or safety, such as donating to unfamiliar callers, wearing a coat in July, or ignoring a stove.
Visual-spatial problems, including misjudging steps, trouble parking, difficulty reading, or not recognizing a familiar face in a photo.
Withdrawal from work, hobbies, church, or family calls, often because keeping up has quietly become hard.
Mood or personality changes that last for weeks: new anxiety, suspicion, apathy, irritability, or uncharacteristic anger.
These ten match the Alzheimer's Association 10 warning signs, reframed for what adult children actually see at home. Seeing your parent in two or three items does not mean they need a specific product or a diagnosis from a blog post. It means you are not alone in what you are noticing, and it is time to start writing things down.
What memory changes are normal aging vs worth a doctor visit?
Normal aging looks like slower recall that recovers: blanking on a neighbor's name and remembering it at dinner, or retelling a story days apart. Concerning memory loss looks like gaps that never close: forgetting a close relative's name, not remembering a call happened, getting lost on a familiar road, or being unable to follow a lifelong recipe. The difference is recovery and frequency.
Normal age-related memory loss, sometimes called age-associated memory impairment, is real and common. Processing speed slows, multitasking gets harder, and names take longer to surface. What does not happen in normal aging is losing whole experiences or the ability to do familiar things.
Use this table as a side-by-side reference. Each row pairs a normal example with the version that warrants a doctor visit.
What you notice | Often normal aging | Worth a doctor visit |
|---|---|---|
Forgetting names | Blanks on a neighbor's name, recalls it later that day | Forgets a close relative's name or who they are |
Repeating stories | Retells the same story days apart | Asks the same question several times in one visit |
Recent conversations | Misses one detail of yesterday's call | Does not remember the call happened at all |
Finding words | Occasional tip-of-the-tongue pause | Substitutes wrong words or stops mid-sentence often |
Time and place | Forgets the date, then works it out | Loses track of the season or where they are |
Familiar tasks | Needs help setting up a new phone | Cannot follow a lifelong recipe or run the washer |
Misplacing items | Loses keys, retraces steps, finds them | Puts keys in the freezer, cannot retrace, blames others |
Bills and mail | A rare late payment | Unpaid stacks, duplicate payments, scam losses |
Driving | Brief hesitation at a highway exit | Lost on a familiar road, new unexplained dents |
Judgment | One questionable purchase | Gives money to callers, dresses for the wrong weather |
Visual-spatial skills | Needs stronger reading glasses | Misjudges steps or curbs, trouble parking or judging distance |
Mood and social life | A bad day after poor sleep | Drops hobbies, church, or calls; persistent suspicion or apathy |
Why does my parent keep repeating the same questions or forgetting conversations?
Repeated questions happen when new information is not being stored. Your parent hears the answer, but the memory of hearing it does not form, so the question feels new to them twenty minutes later. Occasional repetition can come from fatigue, grief, or anxiety. The concerning signal is frequency plus no awareness that the question was already asked and answered.
Families usually notice repetition first because it happens in real time. Your mother asks whether you are coming Sunday, then asks again before the call ends. Your father retells a story from the news twice in one sitting.
Short-term memory relies on the hippocampus, which is affected early in Alzheimer's disease. That is why recent events slip while decades-old memories remain sharp and detailed.
What to do: write down two or three examples with dates and how many times the question came back. Bring them to the primary care visit instead of debating memory at the kitchen table.
What is mild cognitive impairment, and is it the same as dementia?
Mild cognitive impairment, or MCI, is a measurable decline in memory or thinking that is greater than normal aging but does not yet interfere with daily independence. A parent with MCI may repeat questions or misplace items yet still manage bills, driving, and medications. MCI is not dementia, and not everyone with MCI progresses to it.
The National Institute on Aging describes MCI as a stage where symptoms are noticeable to the person and to family, but daily function stays mostly intact. That middle ground is where most adult children first start searching.
The Alzheimer's Association reports that roughly 10 to 15 percent of people with MCI progress to dementia each year. That also means many remain stable for years, and some improve when a treatable cause is found.
Naming the stage matters. If your parent's doctor says MCI, ask what type (amnestic or non-amnestic), what caused it, and how often cognition will be rechecked. Annual follow-up is typical.
Can memory loss in an aging parent be reversed?
Yes, when the cause is treatable. Medication side effects, thyroid problems, vitamin B12 deficiency, depression, urinary tract infections, hearing loss, sleep apnea, heavy alcohol use, and dehydration can all produce memory loss that improves once addressed. Alzheimer's and most other dementias are not reversible, which is exactly why a doctor should rule out the fixable causes first.
The Mayo Clinic memory loss guide lists these reversible contributors, and in our experience families are surprised how often one of them is involved. Here is what to ask the doctor to check so you can advocate at the appointment:
Medication review: sleep aids, anticholinergic bladder or allergy drugs, benzodiazepines, and some pain medications can cloud memory. Ask the doctor to review every prescription and over-the-counter product against the Beers Criteria for older adults.
Thyroid panel (TSH): an underactive thyroid slows thinking and mood.
Vitamin B12 and folate: low levels cause memory loss, fatigue, and numbness, and are common in people taking metformin or acid reducers.
Depression screen (PHQ-9 or GDS): late-life depression often looks like forgetfulness, apathy, and withdrawal rather than sadness.
Infection check: a urine test if confusion appeared quickly, especially with a fever or new incontinence.
Hearing and vision test: a parent who cannot hear the question cannot remember the answer. Hearing loss is one of the largest modifiable dementia risk factors.
Sleep history: untreated sleep apnea and chronic insomnia both impair memory.
Alcohol and hydration: both are easy to overlook and quick to correct.
If the workup finds a cause, memory can improve within weeks of treatment. If it finds nothing, you have ruled out the easy answers and can move to a fuller cognitive evaluation with a clearer picture.
What does sudden confusion mean, and when is it an emergency?
Sudden confusion that develops over hours or days is delirium until proven otherwise, and it is a medical emergency, not an early sign of dementia. Common triggers include infection, a new medication, dehydration, or stroke. Gradual decline over months is the pattern of memory loss. Abrupt change in alertness, speech, or attention needs same-day care.
Utah Health and other clinical sources lead with this distinction because families confuse the two. Dementia creeps. Delirium arrives.
Call 911 for face drooping, arm weakness, slurred speech, a fall with head injury, or a parent who is suddenly very drowsy or agitated and cannot focus. Call the doctor the same day for new confusion with fever, pain, or urinary symptoms.
Sundowning is different again. It is a predictable late-afternoon or evening increase in confusion, restlessness, or agitation in someone who already has cognitive impairment. It is not an emergency, but it is worth reporting, because lighting, daytime activity, and a steady evening routine reduce it.
What home clues show that memory loss is affecting independence?
Functional clues show up where memory and attention work hardest: finances, medications, driving, food, and self-care. Watch for unopened mail and shut-off notices, duplicate payments, pill organizers with missed or doubled days, unexplained dents in the car, spoiled food in the fridge, weight loss, and declining hygiene. These signs mean memory loss has started to touch safety.
Compare everything to your parent's baseline. A father who always balanced the checkbook to the penny and now has three overdraft notices is a different signal than a father who never liked paperwork.
A quick walkthrough during your next visit tells you a lot. Open the fridge and check dates. Look at the pill organizer against the calendar. Glance at the mail pile, the stove knobs, and the car bumper. Notice whether clothes are clean and whether the same outfit appears several days running.
If your parent lives alone, long stretches without conversation also reduce stimulation and hide decline. Our guide to check-in services for elderly parents living alone explains how daily calls catch mood and routine changes between your visits.
None of these clues prove a diagnosis. They do justify a doctor visit and a conversation about support at home.
What is the 2 finger test for dementia, and do at-home tests work?
The 2 finger test is a social media challenge where a parent copies hand and finger positions shown by someone else. It loosely resembles the interlocking finger test clinicians sometimes use to check visual-spatial processing, but it has not been validated as a stand-alone dementia screen. Validated brief tools exist, yet even those only flag who needs a full evaluation.
Here is how the common at-home and office screens compare:
2 finger test: a video trend, not a clinical instrument. Failing it proves nothing; passing it rules out nothing.
Clock-drawing test: the parent draws a clock face showing a specific time, such as ten past eleven. Misplaced numbers or hands can signal visual-spatial or executive trouble. It is one piece of a screen, never a verdict.
Mini-Cog: three-word recall plus the clock drawing, taking about three minutes. Used by many primary care doctors, including during the Medicare annual wellness visit, which includes a required cognitive assessment.
SAGE test: the Self-Administered Gerocognitive Exam from Ohio State is a free pen-and-paper test that takes about 15 minutes at home. It is designed to be completed and then brought to a physician for scoring, not interpreted at the kitchen table.
MoCA and MMSE: longer office screens a clinician administers and interprets.
Every one of these is affected by education, hearing, vision, anxiety, and a bad night's sleep. A low score is a reason to book an evaluation, not a diagnosis. A normal score does not cancel out the patterns you have been seeing at home.
What happens at a memory evaluation, and how should you prepare?
A memory evaluation includes a detailed history from the patient and a family member, a cognitive screen such as the Mini-Cog or MoCA, a physical and neurological exam, bloodwork for thyroid, B12, and metabolic problems, and often a brain CT or MRI. Some patients are referred for longer neuropsychological testing. Preparation is a symptom log and a complete medication list.
Early diagnosis matters for three reasons. Treatable causes get fixed sooner. Families can plan finances, driving, and living arrangements while the parent can still participate. And some newer Alzheimer's treatments are only considered in the earliest stages, so timing affects options.
The National Institute on Aging explains that doctors rely heavily on what family members report, because the parent may not recall the episodes. Your notes are evidence.
Copy this symptom log into a note on your phone or print it. One line per event, for two to four weeks before the appointment.
Date | What happened | Specific example | How often this week | Effect on safety or routine |
|---|---|---|---|---|
Mar 3 | Repeated question | Asked when I was arriving four times in one call | Daily | None yet, but new |
Mar 6 | Medication error | Tuesday and Wednesday pills still in organizer on Thursday | Twice this month | Blood pressure medication missed |
Mar 9 | Got lost driving | Called from a gas station, could not find the way home from church | First time | Driving safety concern |
IMAGE TAG: A middle-aged son at a dining table writing dates and short notes in a small notebook beside a weekly pill organizer and a cup of tea, soft window light, calm and focused expression.
Bring the log, a list of every medication and supplement, and a note on sleep, mood, alcohol, hearing, and any recent illness or hospitalization. Ask to attend the appointment, and ask your parent to sign a release so the office can speak with you afterward. Our list of dementia questions to ask the doctor covers what to raise once results come back.
How do you talk to a parent who denies memory problems?
Start with one specific observation, not a label, and tie the visit to something your parent already values. Say "you asked about Sunday four times on our last call, and I want to make sure nothing simple like a medication is causing it" rather than "I think you have dementia." Keep it private, keep it short, and offer to handle scheduling.
Defensiveness is normal. Memory loss is frightening, and most parents are more aware than they admit. A few scripts that lower the temperature:
The routine frame: "Your Medicare wellness visit includes a memory check for everyone over 65. Let's get it done and have one less thing to wonder about."
The reversible frame: "A lot of this can come from thyroid, B12, or a sleep problem. I'd rather find something fixable than guess."
The ally frame: "I'm not trying to take anything over. I want you to stay in your house as long as possible, and this helps us do that."
Some parents genuinely cannot perceive their own decline. This is called anosognosia, and it is a symptom of the condition, not stubbornness. Arguing will not create insight. Instead, work with the doctor directly, share your log ahead of the visit, and let the clinician raise the topic.
Involve siblings early. Agree on who attends appointments, who manages the log, and who handles money questions. Mixed messages from different adult children give a defensive parent a reason to dismiss all of them.
If your parent refuses outright, do not force it in one conversation. Note the refusal, keep logging, and revisit after the next concerning event. A safety incident often changes the answer.
When can Velma help after a doctor visit?
Velma helps once a physician has ruled out treatable causes, confirmed early memory loss, and agreed your parent is safe at home. Velma is a research-backed cognitive health program at $199 a month, as of October 2026, that pairs AI assistants with dedicated care managers for daily cognitive sessions, routine support, and family alerts. It is not a diagnosis tool, emergency monitoring, or a substitute for clinical care.
After the evaluation, the question becomes what the days look like. Daily structure helps: regular conversation, gentle routine reminders, cognitive exercise, and family visibility when patterns shift. Our guide to a daily routine for dementia patients explains why consistency reduces confusion.
Velma fills that daily layer without putting the adult child on every call. Each session is a cognitive exercise and a routine check. The program adjusts weekly based on individual progress, and families receive regular updates and alerts when mood, confusion, or routine changes. The protocols are guided by speech pathologists, neurologists, and dementia care specialists.
Two results shared by the program show what daily structure can do. Roy, a musician with early Alzheimer's, became happier and more outgoing and started participating in social events again, which reduced strain on his wife, a nurse. Dara, an independent retiree with Alzheimer's, doubled her attention and working memory in a few weeks, had more daily energy, started going to the gym, and saw her anxiety decrease significantly.
Pros families look for
Daily cognitive sessions and routine support without requiring family involvement
A dedicated human care manager alongside the AI assistants, with 24/7 support
Family alerts and regular updates when mood or cognition patterns change
Weekly program adjustments based on your parent's progress
$199 a month, less than a single in-person therapy session
Cons and honest limits
Not a diagnosis tool, fall detector, or emergency monitoring
Requires a parent willing to take phone sessions
Medical decisions stay with licensed clinicians
Best for: families whose physician has confirmed early memory loss or early Alzheimer's and whose parent is safe at home but needs daily engagement, structure, and visibility between visits.
Suggested Article: